Section 01 of 20
Introduction
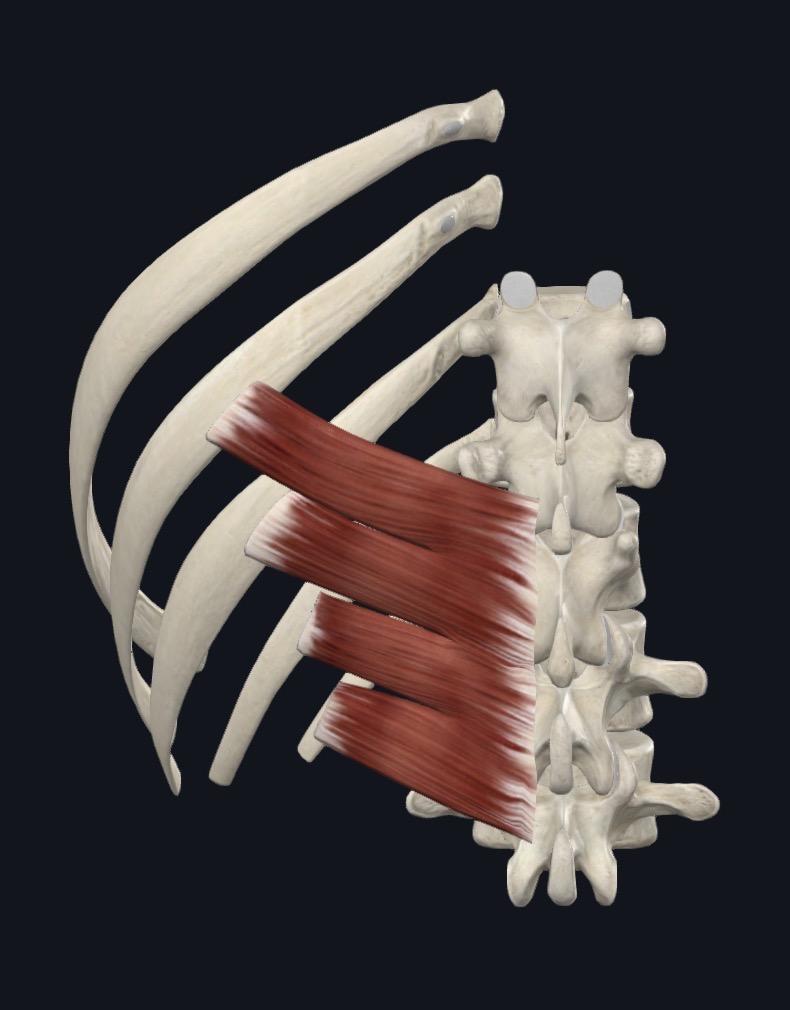
Serratus posterior inferior is a thin, flat, quadrilateral muscle in the lower back, deep to the latissimus dorsi. It runs upward and outward from the lower thoracic and upper lumbar spinous processes to the lower four ribs, where it ends in finger-like (serrated) slips, which give the muscle its name.
It is much smaller and less powerful than the erector spinae and latissimus dorsi that surround it. Its main job is to steady and pull down the lower ribs, working against the diaphragm and helping control the rib cage during breathing.
Section 02 of 20
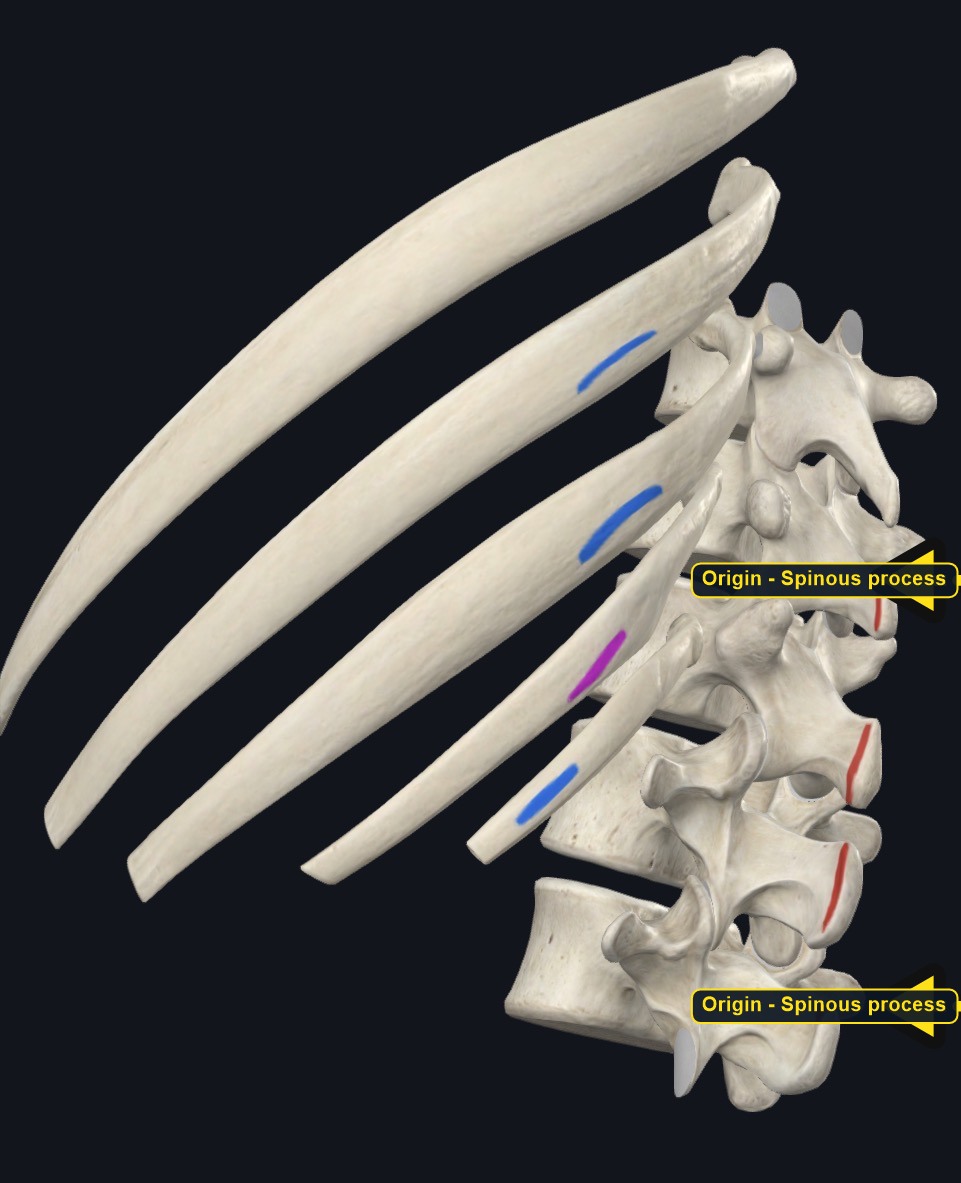
Origin
| Origin | The spinous processes of the lower two thoracic and upper two or three lumbar vertebrae (about T11–L3) and the supraspinous ligament, by a thin aponeurosis shared with latissimus dorsi and the lower serratus posterior superior region. |
|---|
Section 03 of 20
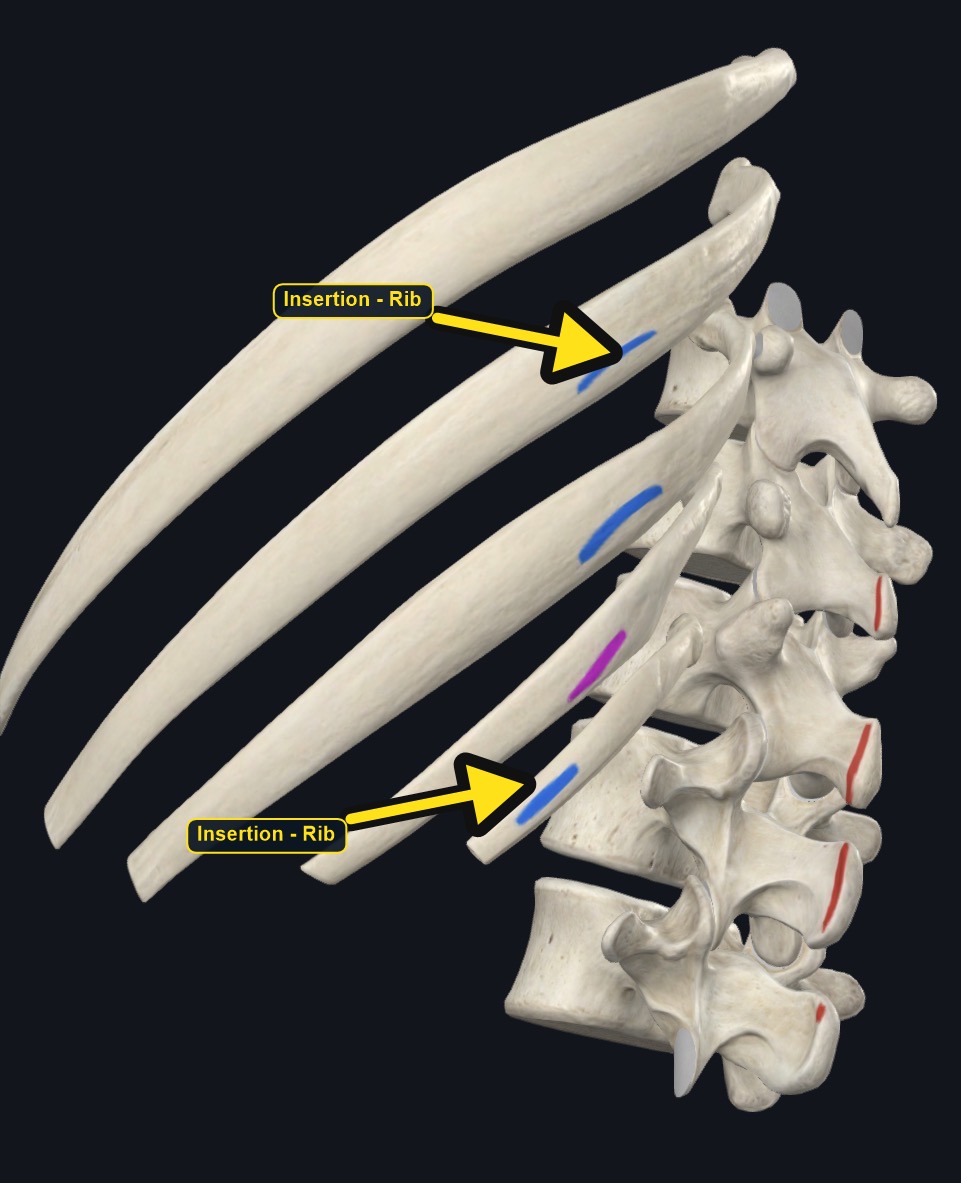
Insertion
| Insertion | The inferior borders of the lower four ribs (ribs 9–12), near their angles. |
|---|
Section 04 of 20
Actions
No dedicated action video is currently available. This movement is explained below and video will be added when verified source media becomes available.
| Primary action | Depression of the lower ribs. |
|---|---|
| Secondary actions | Stabilizing the lower ribs against the diaphragm during breathing. |
| Movement at the joint | Costovertebral joints of ribs 9–12. |
| Heads / fiber groups | Single thin quadrilateral sheet. |
| Functional examples | Forceful exhalation; coughing and sneezing; singing; playing a wind instrument. |
Depression of the lower ribs
Pulls the lower four ribs downward and backward.
Stabilizing the rib cage during breathing
Opposes the pull of the diaphragm on the lower ribs, helping keep them steady during forceful inhalation and exhalation.
Possible proprioceptive role
Some sources describe it as having a sensory or proprioceptive function related to rib and trunk position, in addition to its small mechanical pull.
Section 05 of 20
Nerve Innervation
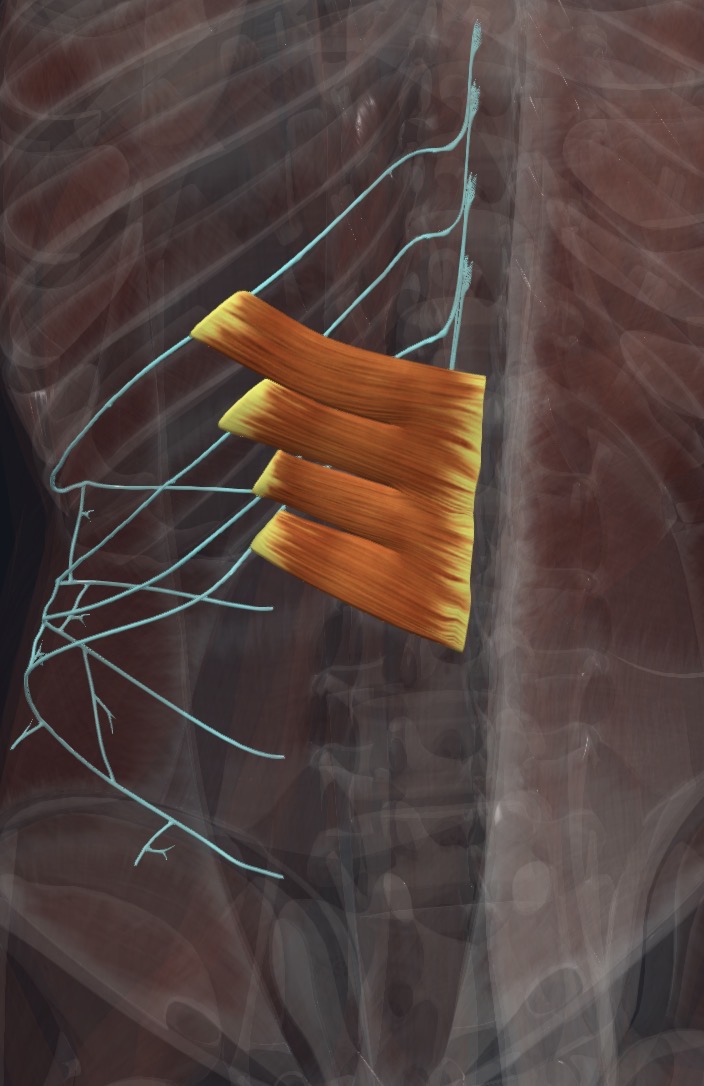
| Nerve | Anterior rami of the lower thoracic spinal nerves, roughly T9–T12. |
|---|
The nerves that supply this muscle are the same intercostal nerves that supply the lower rib and abdominal wall region. Sharp band-like pain along a rib, or pain that follows a rib's path, may reflect an intercostal nerve or rib problem, not only muscle tightness.
Section 06 of 20
Blood Supply
| Blood | Posterior intercostal arteries and branches of the subcostal artery. |
|---|
Section 07 of 20
Pictures and Visual Anatomy
Section 08 of 20
Functional Movement
Serratus posterior inferior is most active during deep or forceful breathing, coughing, sneezing, singing, and activities like playing a wind instrument, where it helps stabilize the lower ribs against the pull of the diaphragm.
Section 09 of 20
Synergists and Antagonists
Synergists: the internal intercostals and the abdominal muscles (rib depression and forced exhalation), and quadratus lumborum for lower rib stability. Antagonists: the diaphragm and the external intercostals (rib elevation during inhalation).
Section 10 of 20
Palpation and Location
Client position and technique
Position the client prone with a pillow under the abdomen. Locate the lower ribs and the spine at the thoracolumbar junction, then feel for the thin sheet of tissue deep to the latissimus dorsi, over the lower ribs. Because it is thin and deep, it is felt more as a subtle change in tissue tension than as a distinct band; ask the client to take a full breath and exhale forcefully to feel subtle rib movement in the area.
Protect nearby structures
The lower ribs, kidneys, and the pleural cavity are close to this region. Use light to moderate pressure, avoid pressing sharply on the ribs, and stop if the client reports sharp pain, difficulty breathing, or pain that feels deep in the flank.
Section 11 of 20
Massage Therapy Relevance
Serratus posterior inferior is a minor contributor to lower back and rib tension, most often considered in singers, wind instrument players, and people with chronic cough. Most lower back pain in this region comes from the erector spinae, quadratus lumborum, thoracolumbar fascia, or the spine itself.
Section 12 of 20
Dysfunction: What Happens When Movement Goes Wrong
Changes in how a muscle works can change how a joint moves. The points below describe possibilities that may be associated with altered muscle function; they are not diagnoses, and one muscle is never assumed to be the sole cause of a problem.
When the muscle is weak
Weakness is difficult to detect on its own; the diaphragm and other rib muscles carry most of the work of breathing.
When it is tight or shortened
Tightness may be associated with a subtle ache at the thoracolumbar junction, hard to distinguish from the surrounding larger muscles.
When it is overused
Prolonged coughing, forceful singing, or heavy breathing may overload the muscle and may contribute to a dull ache in the lower back and ribs.
When it is strained
A strain is uncommon and mild; persistent or severe pain in this area more often points to the ribs, spine, or kidney.
When it is inhibited or others compensate
Reduced activation is difficult to detect clinically, given its small size and overlap with larger rib and back muscles.
When it does not coordinate well with synergists and antagonists
Poor coordination with the diaphragm and the abdominal muscles may be associated with inefficient breathing mechanics.
Section 13 of 20
Conditions, Pathologies, and Pain Relationships
Minor strain from forceful breathing
Prolonged coughing, forceful singing, or heavy breathing during illness or exercise may be associated with a dull ache at the thoracolumbar junction.
Overlap with thoracolumbar tension
Because it lies deep to the erector spinae and latissimus dorsi, its contribution to back pain is hard to separate from these larger, more commonly involved muscles.
Rib-related pain
Tenderness near the lower rib attachments may sometimes be associated with rib or intercostal irritation rather than the muscle itself.
Differential considerations
Kidney problems, thoracolumbar disc and facet joint pain, rib dysfunction, and lung conditions can all cause pain in this region.
Section 14 of 20
Example Clinical Relationship
A singer reports a mild ache at the base of the rib cage after a long rehearsal involving controlled, forceful breathing. Serratus posterior inferior may be a minor contributor, along with the surrounding back and rib muscles, and the pattern may be associated with overuse from breath control work, but kidney, rib, and spine problems can look similar. Gentle work in the region may support comfort, while flank pain with fever or sharp rib pain with breathlessness needs referral.
Section 15 of 20
Massage and Treatment Approaches
For healthy, non-acute tissue, position the client prone with the abdomen supported. Begin with broad effleurage over the thoracolumbar junction, then use gentle kneading through the more superficial latissimus dorsi and erector spinae, working with the client's breathing and within comfortable pressure.
| Movement | Use gentle diaphragmatic breathing and trunk rotation within comfort. |
|---|---|
| Regional work | Consider latissimus dorsi, the erector spinae, quadratus lumborum, and the thoracolumbar fascia when assessment supports it. |
| Avoid | Deep pressure directly on the lower ribs or the flank, over an acute injury, or at any point that reproduces sharp pain. |
Section 16 of 20
Precautions and Contraindications
Precautions and contraindications
- Acute rib injury, suspected fracture, or recent thoracic or abdominal surgery.
- Use caution with severe osteoporosis, anticoagulant use, or easy bruising.
- Avoid deep pressure over the lower ribs and flank.
- Stop if pressure causes sharp pain or breathing discomfort.
Section 17 of 20
Red Flags and When to Refer
Red flags and referral
- Sudden sharp chest or rib pain with shortness of breath (possible rib fracture or lung problem).
- Flank pain with fever, blood in the urine, or burning urination (possible kidney problem).
- Back pain with fever, unexplained weight loss, or night pain.
- Numbness in the saddle area or bladder or bowel changes with back pain.
Section 18 of 20
Study Summary
Attachments
Origin: T11–L3 spinous processes. Insertion: lower borders of ribs 9–12.
Actions
Depresses the lower ribs and stabilizes them against the diaphragm during breathing.
Supply
Anterior rami of T9–T12; posterior intercostal and subcostal arteries.
Section 19 of 20
Instructor Narration
Open narration transcript
Serratus posterior inferior is a thin, deep muscle of the lower back, hidden beneath the latissimus dorsi.
It arises from the spinous processes of the lower two thoracic and upper lumbar vertebrae and inserts, by finger-like slips, on the lower four ribs.
It pulls the lower ribs down and back and helps steady them against the pull of the diaphragm during breathing. The internal intercostals and abdominal muscles help it, and the diaphragm and external intercostals oppose it.
The lower thoracic intercostal nerves supply it, from about T9 to T12, and the posterior intercostal and subcostal arteries provide its blood.
Palpate at the thoracolumbar junction, deep to the latissimus dorsi, using light to moderate pressure, and notice subtle changes with a full breath.
Its own contribution to back pain is minor and hard to separate from the erector spinae, quadratus lumborum, and thoracolumbar fascia around it, and kidney, rib, and lung problems can also cause pain here. Refer sudden sharp rib pain with breathlessness, flank pain with fever, or back pain with fever or weight loss.
Remember: T11 to L3 spinous processes to ribs 9 to 12; depresses the lower ribs; lower intercostal nerves T9 to T12.
Section 20 of 20