Section 01 of 20
Introduction
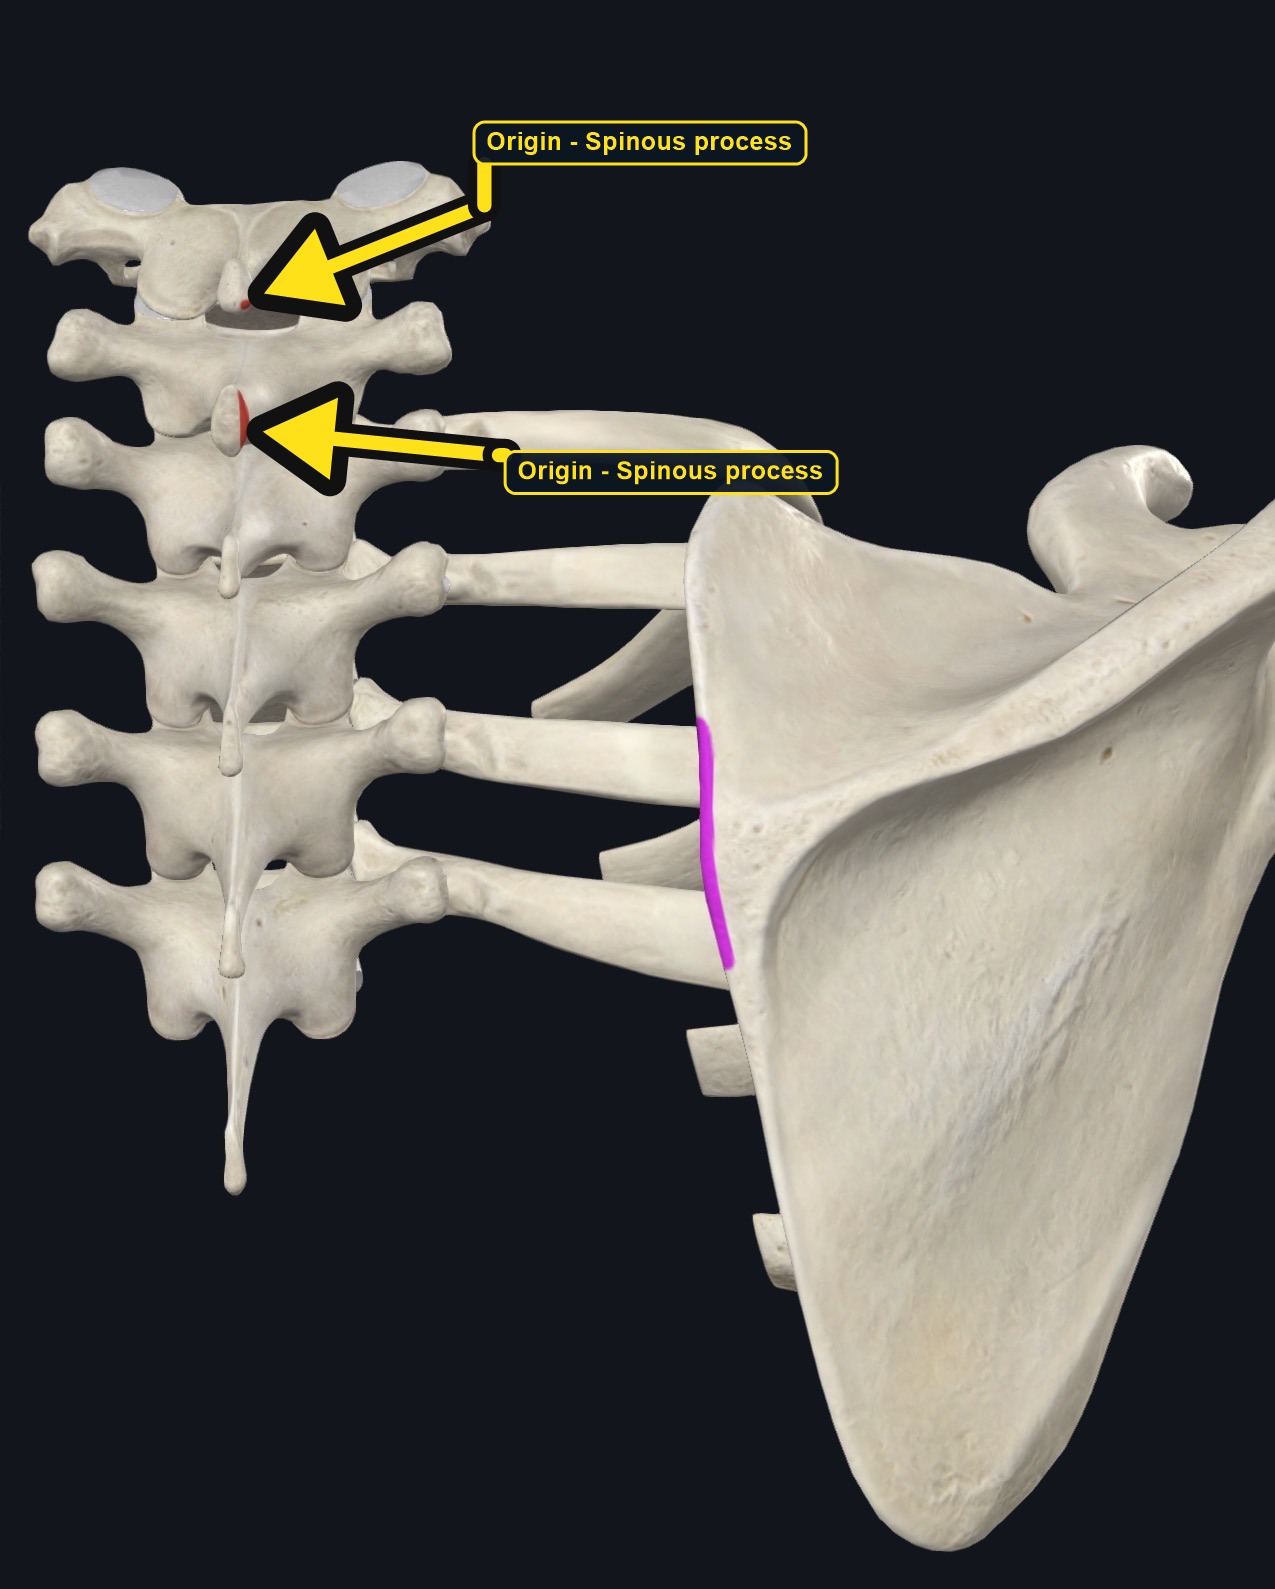
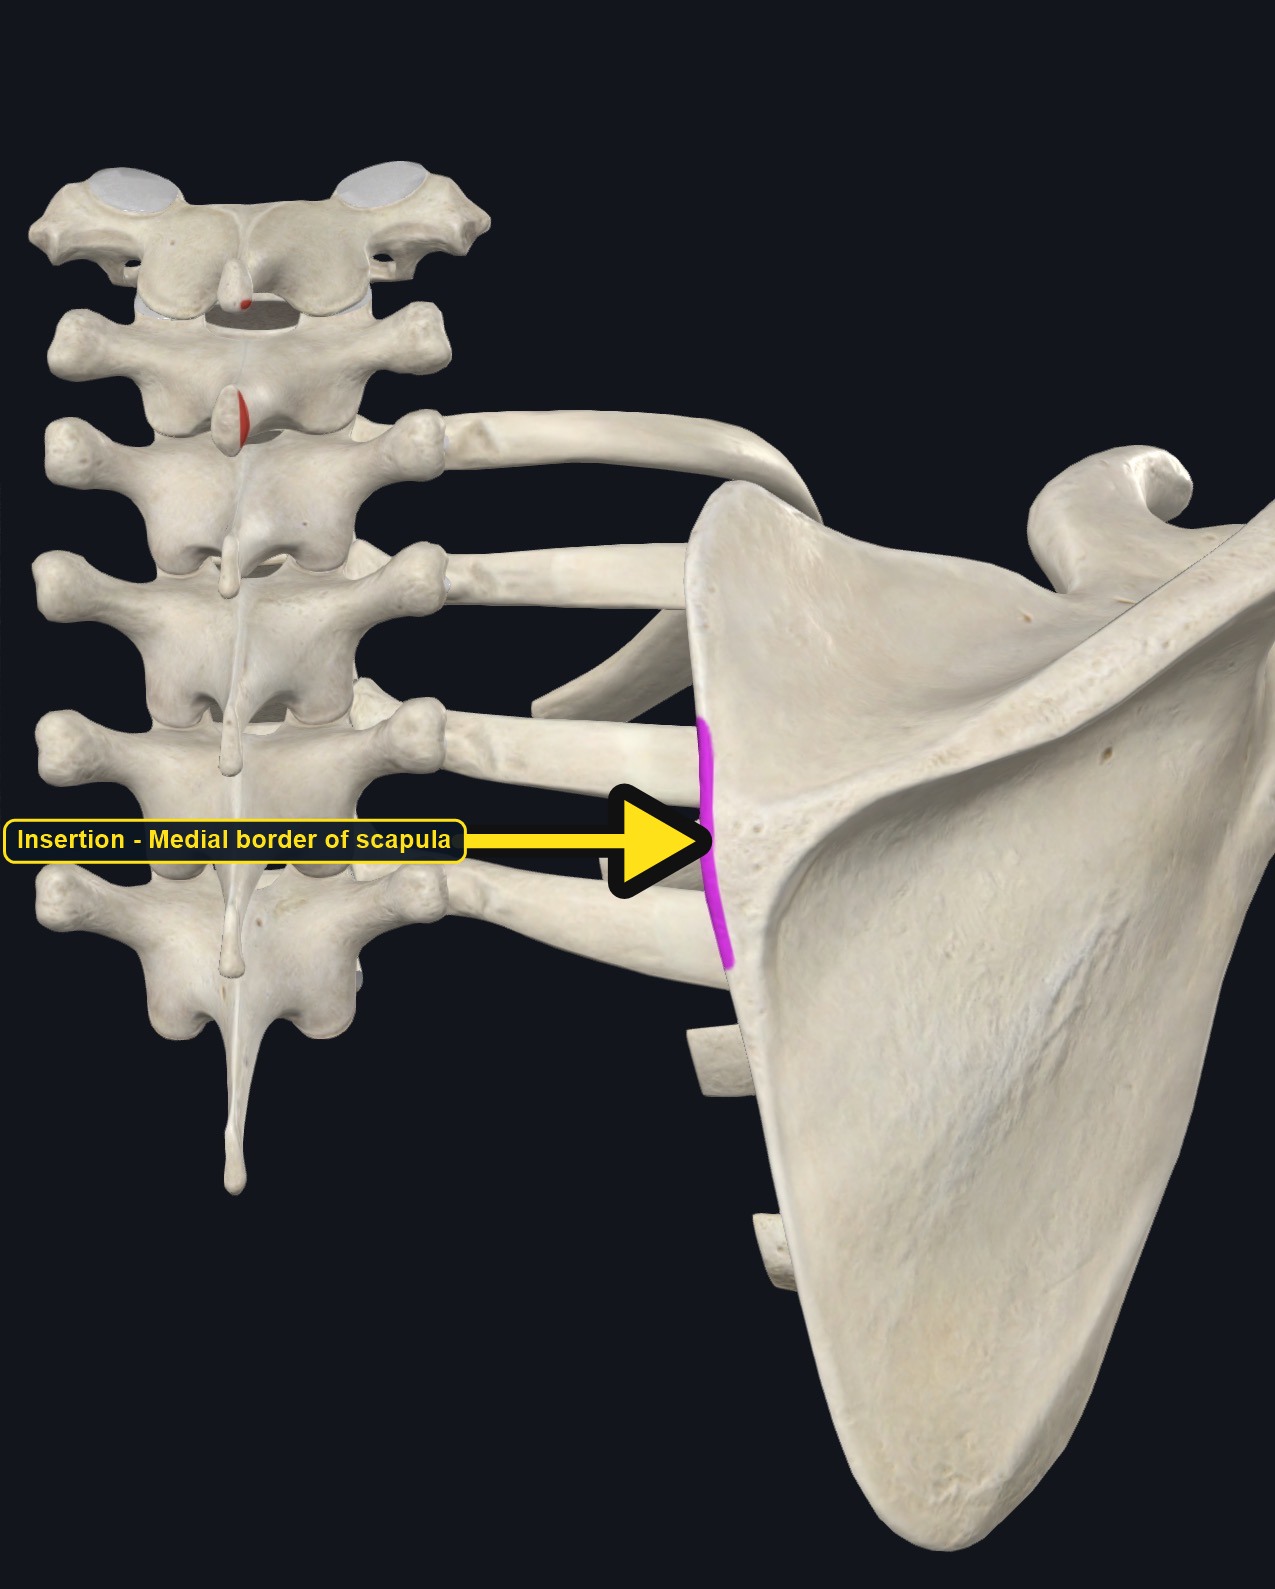
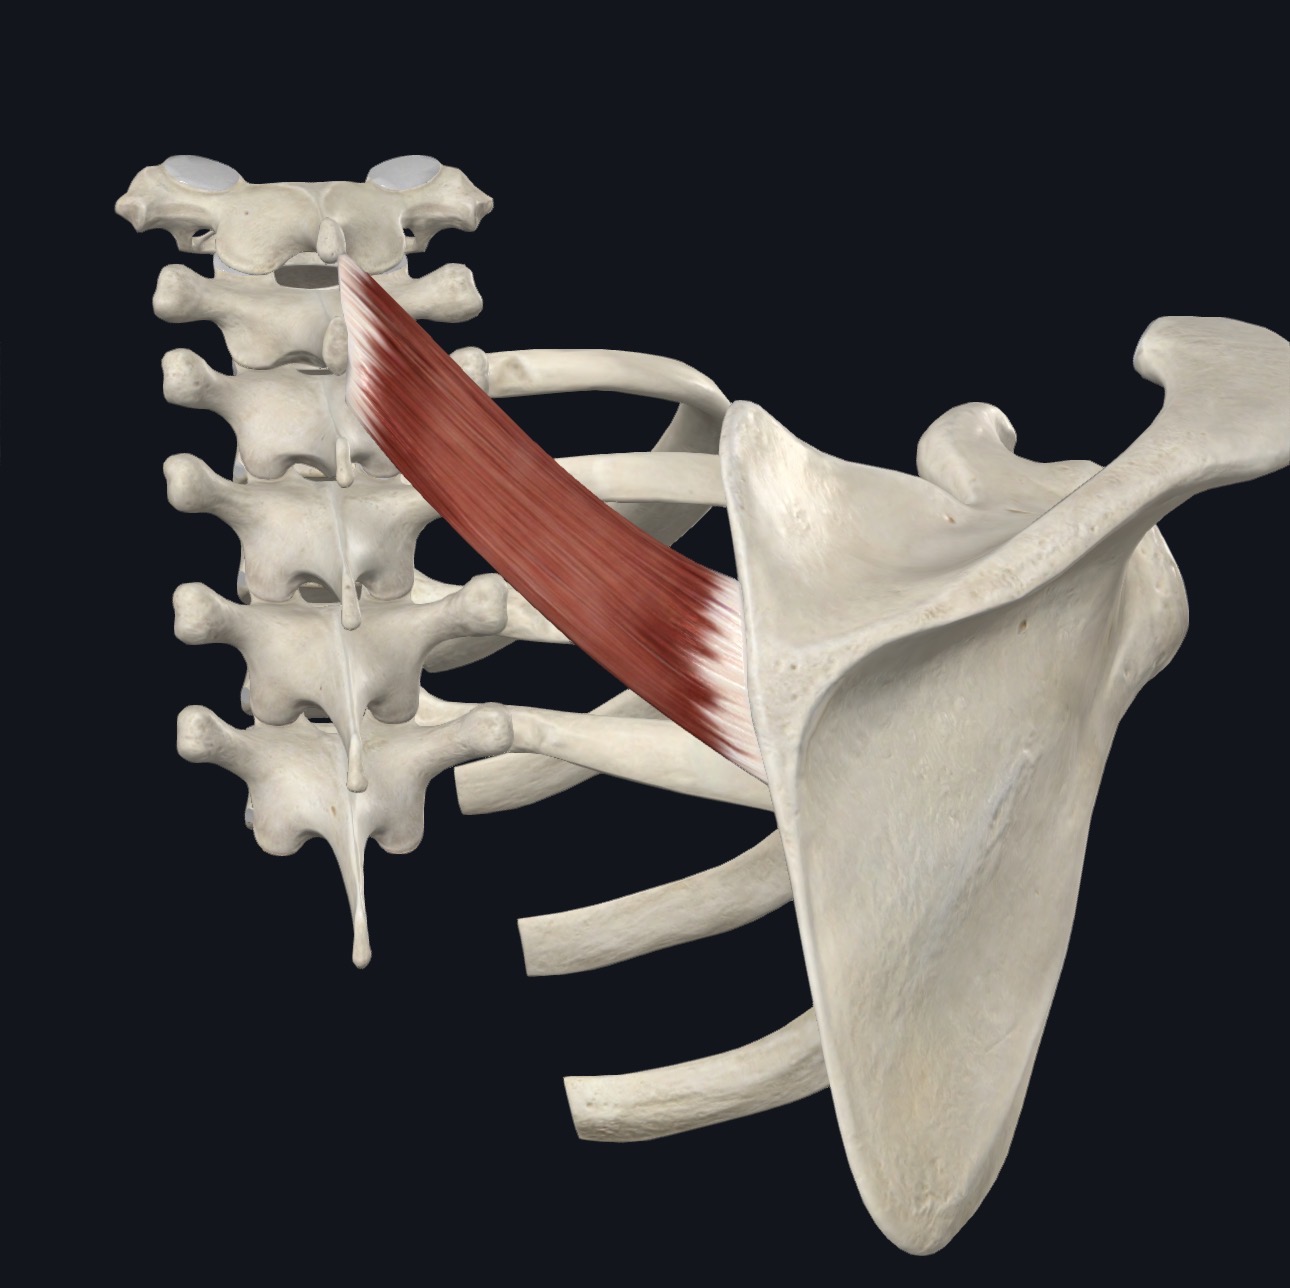
Rhomboid minor is a small, thin, parallelogram-shaped muscle in the upper back. It lies just above rhomboid major and runs down and outward from the lower part of the nuchal ligament and the spinous processes of C7 and T1 to the medial border of the scapula at the level of the spine of the scapula.
A thin layer of connective tissue often separates it from rhomboid major, and the two are sometimes described as one muscle. Together they retract the scapula and hold it against the chest wall.
Section 02 of 20
Origin
| Origin | The lower part of the nuchal ligament and the spinous processes of C7 and T1. |
|---|
Section 03 of 20
Insertion
| Insertion | The medial border of the scapula at the root of the spine of the scapula, above the insertion of rhomboid major. |
|---|
Section 04 of 20
Actions
No dedicated action video is currently available. This movement is explained below and video will be added when verified source media becomes available.
| Primary action | Retraction of the scapula. |
|---|---|
| Secondary actions | Downward rotation of the scapula, slight elevation, and stabilization against the rib cage. |
| Movement at the joint | Scapulothoracic movement. |
| Heads / fiber groups | Single small muscle, smaller and higher than rhomboid major. |
| Functional examples | Rowing; pulling; squeezing the shoulder blades together; reaching behind the back; sitting upright. |
Scapular retraction
Pulls the scapula toward the spine.
Elevation and downward rotation
Lifts the scapula slightly and rotates the socket downward as the arm is lowered.
Stabilizing the scapula
Holds the scapula against the rib cage during arm movement.
Section 05 of 20
Nerve Innervation
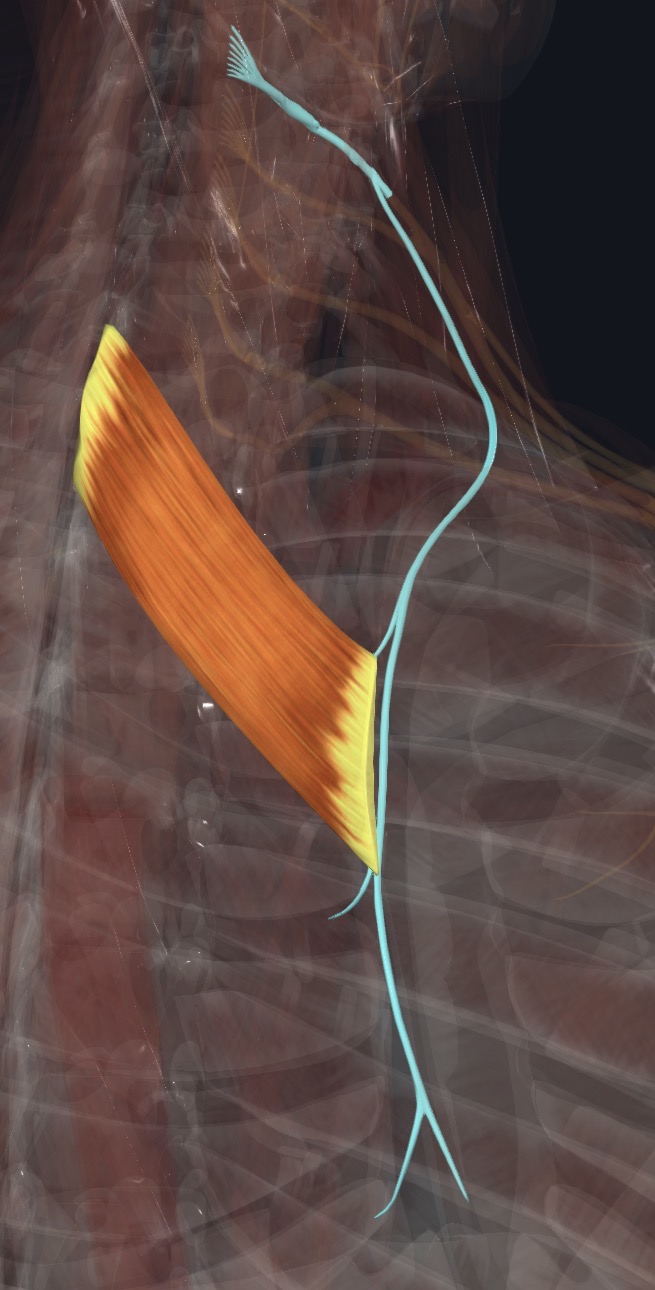
| Nerve | Dorsal scapular nerve, roots C4–C5 (mainly C5). |
|---|
The dorsal scapular nerve passes through the scalene muscles before reaching the rhomboids. Weakness of scapular retraction with pain along the medial border of the scapula may reflect a nerve problem, not only muscle tightness.
Section 06 of 20
Blood Supply
| Blood | The dorsal scapular artery (the deep branch of the transverse cervical artery), with branches of the posterior intercostal arteries. |
|---|
Section 07 of 20
Pictures and Visual Anatomy
Section 08 of 20
Functional Movement
Rhomboid minor works with rhomboid major when rowing, pulling, reaching behind the back, keeping the shoulders back in posture, and holding the shoulder blade steady while the arm moves or carries a load.
Section 09 of 20
Synergists and Antagonists
Synergists: rhomboid major, the middle trapezius (retraction), and levator scapulae (elevation and downward rotation). Antagonists: serratus anterior and pectoralis minor (protraction), and the upper and lower trapezius for upward rotation.
Section 10 of 20
Palpation and Location
Client position and technique
Position the client prone with the arm relaxed, or seated. Locate the spine of the scapula and follow it to the medial border, then move up slightly along the border and toward the lower neck spinous processes. Ask the client to squeeze the shoulder blades together, or to place the hand on the low back and lift, to feel the small muscle tighten deep to the trapezius.
Protect nearby structures
Use light to moderate pressure over this small area. Avoid pressing hard on the spinous processes and ribs, and stop if the client reports sharp pain, tingling, or pain that feels deep in the chest.
Section 11 of 20
Massage Therapy Relevance
Rhomboid minor is often tender at the top of the shoulder blade and lower neck, and it is commonly involved in the upper back tension that comes with rounded-shoulder posture and desk work. Pain in this area can also arise from the neck, the ribs, and internal organs.
Section 12 of 20
Dysfunction: What Happens When Movement Goes Wrong
Changes in how a muscle works can change how a joint moves. The points below describe possibilities that may be associated with altered muscle function; they are not diagnoses, and one muscle is never assumed to be the sole cause of a problem.
When the muscle is weak
Weakness may be associated with rounded shoulders and poor control of the top of the shoulder blade during pulling.
When it is tight or shortened
Tightness may be associated with a pinched feeling near the top of the shoulder blade and limited protraction.
When it is overused
Repeated pulling and sustained shoulder retraction may overload the muscle and may contribute to interscapular and lower neck ache.
When it is strained
A strain may cause sharp pain near the top of the medial border of the scapula; neck and rib problems can look similar.
When it is inhibited or others compensate
Reduced activation may be associated with more work by the upper trapezius and levator scapulae.
When it does not coordinate well with synergists and antagonists
Poor coordination with the trapezius, serratus anterior, and rhomboid major may alter scapular position and may be associated with shoulder and upper back symptoms.
Section 13 of 20
Conditions, Pathologies, and Pain Relationships
Rhomboid strain and tenderness
Sudden pulling, heavy lifting, and prolonged forward posture may be associated with a dull or sharp ache near the top of the medial border of the scapula.
Overstretched and weak muscle
Long periods of rounded shoulders may keep the rhomboids lengthened and may be associated with poor scapular control.
Dorsal scapular nerve involvement
Compression through the scalenes may weaken the muscles and cause a burning pain along the medial border of the scapula.
Differential considerations
Cervical radiculopathy, facet joint problems, rib joint dysfunction, rotator cuff conditions, and referred pain from the heart, lungs, or gallbladder can cause pain in this area.
Section 14 of 20
Example Clinical Relationship
A client who works at a computer reports a tender spot near the top inside corner of the shoulder blade, worse when the shoulders round forward. Rhomboid minor may be involved, and the pattern may be associated with postural strain, but neck, rib, and nerve problems can look similar. Gentle work along the fibers may support comfort, while chest pressure, fever, or progressive weakness needs referral.
Section 15 of 20
Massage and Treatment Approaches
For healthy, non-acute tissue, position the client prone or seated with the arm relaxed. Begin with broad effleurage over the upper back and lower neck, then use gentle kneading and slow strokes along the fibers, and gently move the arm across the chest within comfort.
| Movement | Use gentle scapular protraction and cross-body arm movement within comfort. |
|---|---|
| Regional work | Consider rhomboid major, the trapezius, levator scapulae, pectoralis minor, and the cervical and thoracic paraspinals when assessment supports it. |
| Avoid | Deep pressure on the spinous processes and ribs, over an acute strain, or at any point that reproduces chest pain or arm tingling. |
Section 16 of 20
Precautions and Contraindications
Precautions and contraindications
- Acute neck or upper back injury, suspected fracture, or recent thoracic or cervical surgery.
- Use caution with severe osteoporosis, anticoagulant use, or easy bruising.
- Avoid strong pressure over the spine and ribs.
- Stop if pressure causes sharp pain, chest discomfort, or arm tingling.
Section 17 of 20
Red Flags and When to Refer
Red flags and referral
- Pain at the top of the shoulder blade with chest pressure, shortness of breath, sweating, or pain that spreads to the jaw or left arm.
- Right shoulder blade pain with nausea, vomiting, fever, or pain after fatty meals (possible gallbladder disease).
- Progressive arm weakness, numbness, or a shoulder blade that is clearly winging.
- Neck or back pain with fever, unexplained weight loss, or night pain.
Section 18 of 20
Study Summary
Attachments
Origin: lower nuchal ligament and C7–T1 spinous processes. Insertion: medial border of the scapula at the spine root.
Actions
Retracts the scapula, rotates it downward, and holds it to the ribs.
Supply
Dorsal scapular nerve (C5); dorsal scapular artery.
Section 19 of 20
Instructor Narration
Open narration transcript
Rhomboid minor is the small muscle above rhomboid major, deep to the trapezius, between the lower neck and the shoulder blade.
It arises from the lower nuchal ligament and the spinous processes of C7 and T1, and inserts on the medial border of the scapula at the root of the spine.
It pulls the scapula toward the spine, rotates it downward, and holds it against the ribs. The rhomboid major and middle trapezius help it, and the serratus anterior and pectoralis minor oppose it.
The dorsal scapular nerve, C5, supplies it, and the dorsal scapular artery provides its blood.
Palpate with the client prone, follow the spine of the scapula to the medial border, and feel for the muscle just above the rhomboid major as the client squeezes the shoulder blades together.
Strain, overstretching, and nerve problems are common, and neck, rib, and organ problems can cause pain in this area. Refer chest pressure, right shoulder blade pain with fever or nausea, progressive weakness, or a winging scapula.
Remember: lower nuchal ligament and C7 to T1 to the medial border of the scapula at the spine root; retraction; dorsal scapular nerve.
Section 20 of 20